
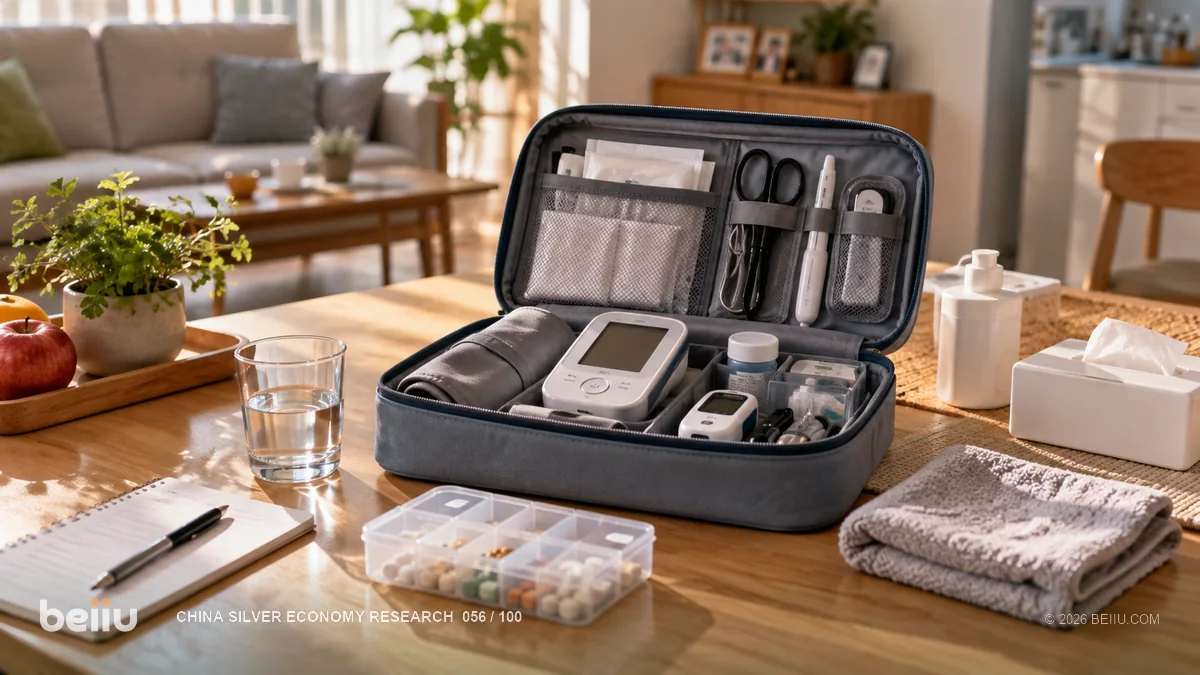
Boundaries of Consumer Technology in Family Chronic Disease Management and Adherence Improvement
Analyzes the role of consumer technology in chronic disease management in home settings, clarifies its boundaries with medical diagnosis, and explores how to improve medication adherence and avoid safety risks through technological means
Conclusion: In home environments lacking professional medical intervention, how can consumer technology assist in chronic disease management while strictly distinguishing its functional boundaries from medical diagnosis to prevent misuse risks
Separate national facts, local variation and analytical inference
Health and care require explicit clinical boundaries and referral paths. This study examines “household medication tasks and professional review” as a reviewable research object: The unit of analysis is one health-related task and its measurement, interpretation, referral and follow-up chain; consumer readings are not diagnoses. In claims about “household medication tasks and professional review”, increased or declined requires a dated comparison and denominator, while mechanism, opportunity and brand judgment remain analytical rather than statistical.
The research question above requires this minimum evidence base: The minimum baseline covers measurement conditions, longitudinal records, medication and disease context, professional review, urgent referral, consent and incomplete follow-up. If “household medication tasks and professional review” lacks an element, the study may state a direction or hypothesis, not a local service volume, procurement quantity or revenue estimate.
Read the fact cards, then verify definitions in the primary material
As of the end of 2024, the population aged 65 and over was 220.23 million, accounting for 15.6%.
Definition source:China National Committee on Ageing: 2024 National Bulletin on the Development of Ageing Programmes
Open primary material ↗Document No. 1 of the General Office of the State Council [2024] proposes a series of economic activities for the silver economy to provide products or services to the elderly and prepare for the elderly stage.
Definition source:General Office of the State Council: Guiding Opinion on Developing the Silver Economy and Improving Older People's Well-being
Open primary material ↗The plan emphasizes coordination among home, community, and institutional care and the combination of medical care and nursing, promoting the coordinated development of elderly affairs and industries.
Definition source:State Council: 14th Five-Year Plan for National Ageing Programmes and Elderly-Care Services
Open primary material ↗Primary sources and use boundaries
China National Committee on Ageing: 2024 National Bulletin on the Development of Ageing Programmes
The 2024 national ageing report records 310.31 million people aged 60 or over (22.0%) and 220.23 million aged 65 or over (15.6%) at year end.
Check source 01 ↗General Office of the State Council: Guiding Opinion on Developing the Silver Economy and Improving Older People's Well-being
The 2024 State Council opinion defines the silver economy as activities that provide products or services to older people and prepare for later life, and calls for scale, standards, clusters and brands.
Check source 02 ↗State Council: 14th Five-Year Plan for National Ageing Programmes and Elderly-Care Services
The 14th Five-Year Plan calls for coordination among home, community and institutional care, integration of medical and wellness services, and coordination between ageing services and industry. It sets system direction, not proof of a project outcome.
Check source 03 ↗National Healthcare Security Administration: 2025 Statistical Bulletin on Healthcare Security Development
The 2025 NHSA bulletin records 308.5476 million long-term-care insurance participants, 1.9291 million beneficiaries and 13,000 designated providers. From 2025, all implementing regions are included, so the count is not directly comparable as growth from the earlier 49-city pilot definition.
Check source 04 ↗General Offices of the CPC Central Committee and State Council: Opinion on Building a Basic Elderly-Care Service System
The basic eldercare service framework emphasises service lists, comprehensive ability assessment, precise identification of people in difficulty, and a shift from people finding services to services finding people.
Check source 05 ↗The fact cards below retain year, geography and source; the source cards return to definitions in the original material. Forecast, research estimate, catalogue listing, policy objective and observed outcome keep different evidence status even when they concern “household medication tasks and professional review”.
Move from correlation to a plausible operating mechanism
Facing a large base of elderly individuals, chronic disease management has become the core of family caregiving. Although policies encourage coordination among home, community, and institutional care, families lack professional diagnostic capabilities, which can easily lead to medication errors. Therefore, the boundaries between consumer technologies (such as smart pillboxes) and medical diagnosis must be clearly defined. The family front line should focus on adherence management and risk warning rather than replacing doctors. The scaled development of the silver economy requires product standardization to ensure that technology safely and effectively assists in chronic disease control in home settings.
Medication safety requires reconciliation, dose and timing, duplicate prescriptions, adherence, symptoms and professional review; reminders are one component. In addition, Measurement quality, longitudinal records, professional interpretation and durable payment jointly shape outcomes. “Develop smart pillboxes with medication recording and abnormal warning functions that interconnect with community health record data” still requires temporal order, alternatives, local conditions and accountable implementation rather than a jump from macro correlation to sales or service effect.
Do not present consumer-device data as diagnosis or treatment effect. A concrete counterexample is: If the system cannot recognise prescription change or a family treats a reminder as proof of administration, more notifications can create false assurance. Until that counterexample to “household medication tasks and professional review” is addressed, the conclusion retains conditions and a bounded scope.
Families, public services and industry change differently
For families, clarifying boundaries can reduce medication risks and enhance caregiver confidence; for the government, promoting standardized products helps implement the integration of medical care and nursing in home settings; for the industry, this provides a path for consumer technology to transform from 'auxiliary tools' to 'health management partners', promoting brand development.
For “household medication tasks and professional review”, households care about time, cost, dignity and continued choice, public bodies must test identification, equity, fiscal durability and incident accountability, and operators must state the workforce, maintenance and compliance required by “Develop smart pillboxes with medication recording and abnormal warning functions that interconnect with community health record data” and who pays for exceptions.
Product teams own measurement boundaries, clinicians own clinical judgment, care services own execution and observation, and the person retains informed choice. Service radius, cost and access for “household medication tasks and professional review” therefore require separate calculations for dense cities, out-migration counties and dispersed rural communities.
Translate the macro judgment into one observable project
Use discharge, medication change, multimorbidity and cognitive change to test who updates the list, confirms administration and acts on omission or duplication. Start with one place, one population and one task, preserving time, cost, failure and family backfill under the current alternative before introducing “Develop smart pillboxes with medication recording and abnormal warning functions that interconnect with community health record data”.
The observation period for “household medication tasks and professional review” includes routine work, holidays, workforce change, unavailable devices or networks, refusal and exit, and requires the project to show whether the population is identified correctly, incidents close, and people, data and essential service recover when the intervention stops.
An opportunity becomes a project only through constraints
- 01Develop smart pillboxes with medication recording and abnormal warning functions that interconnect with community health record data
Before turning “Develop smart pillboxes with medication recording and abnormal warning functions that interconnect with community health record data” into a project, define place, population and the current alternative, then establish a comparable baseline for “measurement conditions”. For “household medication tasks and professional review”, need does not prove that households, institutions or public budgets can pay sustainably.
- 02Establish a family chronic disease management knowledge base to assist caregivers in identifying potential medication conflicts through AI
Validation of “Establish a family chronic disease management knowledge base to assist caregivers in identifying potential medication conflicts through AI” names the user, payer, operator and maintainer separately. If “household medication tasks and professional review” relies on permanent extra responsibility from pilot staff, the observed effect is unlikely to survive scale.
- 03Develop simplified health management interfaces tailored for elderly individuals to reduce usage barriers caused by the digital divide
Test this direction against the counterexample “Data interfaces must comply with medical information security standards to prevent sensitive health data from leaking in home networks”. “household medication tasks and professional review” should move forward only if “professional review” still improves after compliance, workforce, maintenance and exit costs are included.
Treat “Develop smart pillboxes with medication recording and abnormal warning functions that interconnect with community health record data” as a proposition. Move forward only when measurement conditions improves against baseline and maintenance, workforce, compliance, payment and exit costs are not transferred to older people or frontline staff.
Put conditions that could overturn the conclusion in the main text
- 01Consumer technology must not cross the line into disease diagnosis and must clearly label its auxiliary nature to avoid misleading users
Turn “Consumer technology must not cross the line into disease diagnosis and must clearly label its auxiliary nature to avoid misleading users” into an entry and stop condition for “household medication tasks and professional review”, naming who checks it, which record governs and when review occurs. If “Develop smart pillboxes with medication recording and abnormal warning functions that interconnect with community health record data” remains constrained, future optimisation is not a substitute for pause.
- 02Chronic disease management in home settings must consider individual differences to avoid health risks caused by 'one-size-fits-all' algorithmic recommendations
This condition changes the scope of “Establish a family chronic disease management knowledge base to assist caregivers in identifying potential medication conflicts through AI”. Stage review of “household medication tasks and professional review” retains non-completion, exit, complaint and excluded-population cases rather than counting only successful entrants.
- 03Data interfaces must comply with medical information security standards to prevent sensitive health data from leaking in home networks
For “Data interfaces must comply with medical information security standards to prevent sensitive health data from leaking in home networks”, compare rules, resources and cost across city, county and rural settings. National material indicates direction; the local decision on “household medication tasks and professional review” still needs field data, accountable owners and an executable alternative.
Put “Consumer technology must not cross the line into disease diagnosis and must clearly label its auxiliary nature to avoid misleading users” into entry and stop criteria. If local data, interviews, complaints or incomplete cases support this counterexample to “household medication tasks and professional review”, narrow, modify or stop rather than discard adverse evidence.
Measure average improvement and who is left out
- 01 · measurement conditions
For “household medication tasks and professional review”, “measurement conditions” retains population, geography, denominator, period and incomplete cases to test “Develop smart pillboxes with medication recording and abnormal warning functions that interconnect with community health record data”, because an average improvement alone is insufficient.
- 02 · continuity
For “household medication tasks and professional review”, report baseline, pilot and post-exit states for “continuity”, including policy, workforce or system-version changes so external effort is not attributed to the intervention.
- 03 · professional review
“household medication tasks and professional review” reads “professional review” at aggregate and high-risk levels, and coverage does not prove equity when low-income, oldest-old, disabled or remote groups are omitted.
- 04 · referral completion
“household medication tasks and professional review” assigns interpretive responsibility for “referral completion”: who produces and reviews data, what triggers action and which record governs disagreement.
- 05 · privacy and consent
For “household medication tasks and professional review”, “privacy and consent” retains population, geography, denominator, period and incomplete cases to test “Establish a family chronic disease management knowledge base to assist caregivers in identifying potential medication conflicts through AI”, because an average improvement alone is insufficient.
measurement conditions, continuity, professional review, referral completion and privacy and consent answer different questions about scale, process, outcome, equity or cost. Each metric for “household medication tasks and professional review” needs a population, denominator, period, version and missing-case record.
Build a durable point of view from evidence
BEIIU emphasizes that the family is the last line of defense in chronic disease management but is by no means a substitute for medical diagnosis. The value of consumer technology lies in improving adherence and safety, not in usurping medical authority. Only under the premise of strictly distinguishing functional boundaries can the silver economy truly serve the health and well-being of elderly individuals.
BEIIU / 辈佑 considers public evidence, scenario constraints and real-world counterexamples together to identify which opportunities can move into product and partnership practice and which conditions require further observation. New primary evidence and field experience will continue to refine that perspective.
Turn macro research into five practical questions
Fact boundary
For “household medication tasks and professional review”, what can national evidence establish, what can it not establish, and which local data are required to answer the opening research question?
Current alternative
Before a new product or service addresses “household medication tasks and professional review”, how do families, communities or institutions complete the task, and what are its time, cost, failure and user-burden baselines?
Minimum test
Choose one bounded setting from “Develop smart pillboxes with medication recording and abnormal warning functions that interconnect with community health record data”, change one material condition, and test “measurement conditions” together with at least one counter-metric.
Counterexample
For “household medication tasks and professional review”, actively look for “Consumer technology must not cross the line into disease diagnosis and must clearly label its auxiliary nature to avoid misleading users”; if it limits “Develop smart pillboxes with medication recording and abnormal warning functions that interconnect with community health record data” locally, narrow the conclusion and decide whether to pause or use another path.
Public accountability
For “household medication tasks and professional review”, name who authorises entry, operates, handles exceptions, maintains data and equipment, and may stop the service; a missing role leaves the proposal as a hypothesis.
The continue, change or stop floor is: Stop the function or claim when readings cannot be interpreted, referral is unavailable, false alerts transfer risk, or the product crosses a medical-device boundary. For “household medication tasks and professional review”, repeat this check at entry, mid-pilot and scale review, updating the conclusion, budget, ownership and exit arrangement.
References
For “household medication tasks and professional review”, this study prioritises original government, public-institution and international sources, retains reference years, and clearly labels forecasts or estimates.
- China National Committee on Ageing: 2024 National Bulletin on the Development of Ageing Programmes ↗
- General Office of the State Council: Guiding Opinion on Developing the Silver Economy and Improving Older People's Well-being ↗
- State Council: 14th Five-Year Plan for National Ageing Programmes and Elderly-Care Services ↗
- National Healthcare Security Administration: 2025 Statistical Bulletin on Healthcare Security Development ↗
- General Offices of the CPC Central Committee and State Council: Opinion on Building a Basic Elderly-Care Service System ↗